

In brief
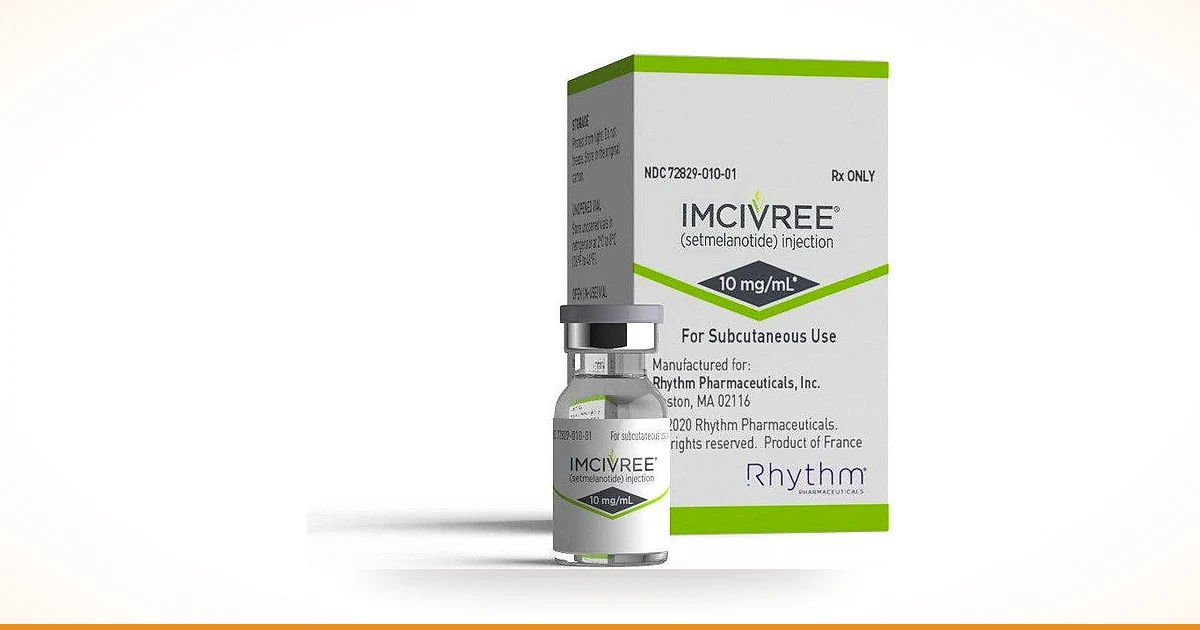
What it is. Setmelanotide (brand name Imcivree, Rhythm Pharmaceuticals) is a prescription melanocortin-4 receptor (MC4R) agonist given as a once-daily subcutaneous injection.
What it is for. Weight reduction and maintenance in rare forms of severe obesity where the MC4R pathway is disrupted — that is, where the satiety signalling mechanism itself is broken.
Who it is NOT for. It is not used in common obesity, obesity with type 2 diabetes or metabolic syndrome. If the MC4R pathway is intact there is nothing to switch on — this is not a "strong weight-loss drug" but the repair of one specific fault.
Indications
| Condition | From age | Requirement |
|---|---|---|
| Acquired hypothalamic obesity — after a tumour, surgery or injury of the hypothalamus | 4 | First approved targeted therapy for the condition; label expanded in 2026 |
| Bardet-Biedl syndrome | 2 | — |
| Obesity due to POMC, PCSK1 or LEPR deficiency | 2 | Genetic confirmation mandatory (pathogenic, likely pathogenic or variants of uncertain significance) |
All three groups share hyperphagia: not a habit of eating a lot, but insatiable hunger in which satiety never physiologically forms. That, rather than the number on the scale, usually defines the severity for patient and family.
Mechanism
The hypothalamus runs a chain that tells the brain energy is sufficient: leptin from adipose tissue → POMC neurons → production of α-melanocyte-stimulating hormone (α-MSH) → activation of MC4R → satiety and normal energy expenditure.
In POMC or PCSK1 deficiency the signalling peptide is never made; in LEPR deficiency leptin is not sensed; after hypothalamic damage the neurons serving the chain are destroyed. The result is identical: MC4R receives no signal, the brain concludes energy is short, and hunger switches on.
Setmelanotide is a synthetic α-MSH analogue. It activates the receptor directly, bypassing the broken link. Hunger falls, calorie intake drops and energy expenditure rises somewhat.
The mechanism carries a built-in consequence: the drug also weakly activates the related MC1R receptor, which governs skin pigmentation. Hence skin darkening — an expected effect rather than a complication.
Dosing and administration
▸ subcutaneous, once daily, usually in the morning;
▸ sites — abdomen, thigh or upper arm, rotated;
▸ supplied as a 10 mg/mL solution in a multiple-dose vial;
▸ the dose is titrated: start low, increase as tolerated.
| Indication and age | Starting dose | Maintenance |
|---|---|---|
| Hypothalamic obesity, from age 4 | 0.5 mg/day | up to 3 mg/day (weight-based under age 6) |
| Bardet-Biedl, POMC/PCSK1/LEPR — adults and from age 12 | 2 mg/day | up to 3 mg/day |
| Same indications, children 6–12 | 1 mg/day | as tolerated |
| Same indications, children 2–6 | 0.5 mg/day | as tolerated |
Kidneys: dose adjustment may be needed in renal impairment; the drug is not recommended in end-stage renal disease. The clinician sets the exact schedule.
What the trials showed
▸ Acquired hypothalamic obesity. In the phase 3 TRANSCEND trial published in the New England Journal of Medicine in 2026, BMI fell by roughly 15–16% over 52 weeks, with no reduction on placebo [1].
▸ Bardet-Biedl syndrome. A phase 3 trial confirmed weight reduction and reduced hyperphagia [2].
▸ POMC and LEPR deficiency. In phase 3 trials a substantial proportion of patients achieved clinically meaningful weight loss, with separately documented reductions in hunger [3].
On durability: the effect persists while treatment continues. After withdrawal weight generally returns — the cause has not gone anywhere; the drug compensates for it rather than removing it.
Adverse effects
Common (20% or more in one or more groups):
▸ skin and mole darkening — a consequence of MC1R activation;
▸ injection-site reactions;
▸ nausea, vomiting, diarrhoea, abdominal pain;
▸ headache;
▸ in men, spontaneous erections without sexual stimulation; in women, changes in arousal;
▸ depression — requires active monitoring throughout treatment.
Requiring particular attention:
| Issue | Why it matters |
|---|---|
| Priapism — an erection lasting over 4 hours | A medical emergency requiring urgent care |
| Mood disturbance, suicidal thoughts | Mental-health monitoring is mandatory, particularly in adolescents |
| Allergic reactions | Standard vigilance for an injectable product |
| Benzyl alcohol in the formulation | Relevant in neonates and very young children |
What to understand before starting
▸ This is treatment for a rare disease, not a weight-loss aid. The diagnosis must be confirmed: genetic testing where POMC, PCSK1 or LEPR deficiency is suspected, documented hypothalamic damage in the acquired form.
▸ Therapy is long-term. Stopping returns the weight.
▸ Skin will darken. Expected, reversible and not dangerous — but it is fairer to agree on it in advance.
▸ Mood must be monitored. Depression sits among the common effects, and the patient population is largely children and adolescents.
▸ It is prescription-only, prescribed and supervised by a clinician, and injections require training for the patient or parents.
Indications and eligibility can be discussed at a consultation; the product can be ordered here and is dispensed on prescription.
References
1. Miller JL, et al. Setmelanotide for the treatment of acquired hypothalamic obesity. N Engl J Med. 2026. PMID 42418774
2. Haqq AM, et al. Efficacy and safety of setmelanotide, a melanocortin-4 receptor agonist, in patients with Bardet-Biedl syndrome and Alström syndrome: a multicentre, randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Diabetes Endocrinol. 2022;10(12):859–868. PMID 36356613
3. Clément K, et al. Efficacy and safety of setmelanotide, an MC4R agonist, in individuals with severe obesity due to LEPR or POMC deficiency: single-arm, open-label, multicentre, phase 3 trials. Lancet Diabetes Endocrinol. 2020;8(12):960–970. PMID 33137293
4. Argente J, et al. Setmelanotide in Bardet-Biedl syndrome: a 52-week comparison of phase 3 trial participants. Obesity (Silver Spring). 2026. PMID 41703984
5. IMCIVREE (setmelanotide) US Prescribing Information, Rhythm Pharmaceuticals.


