

Key points
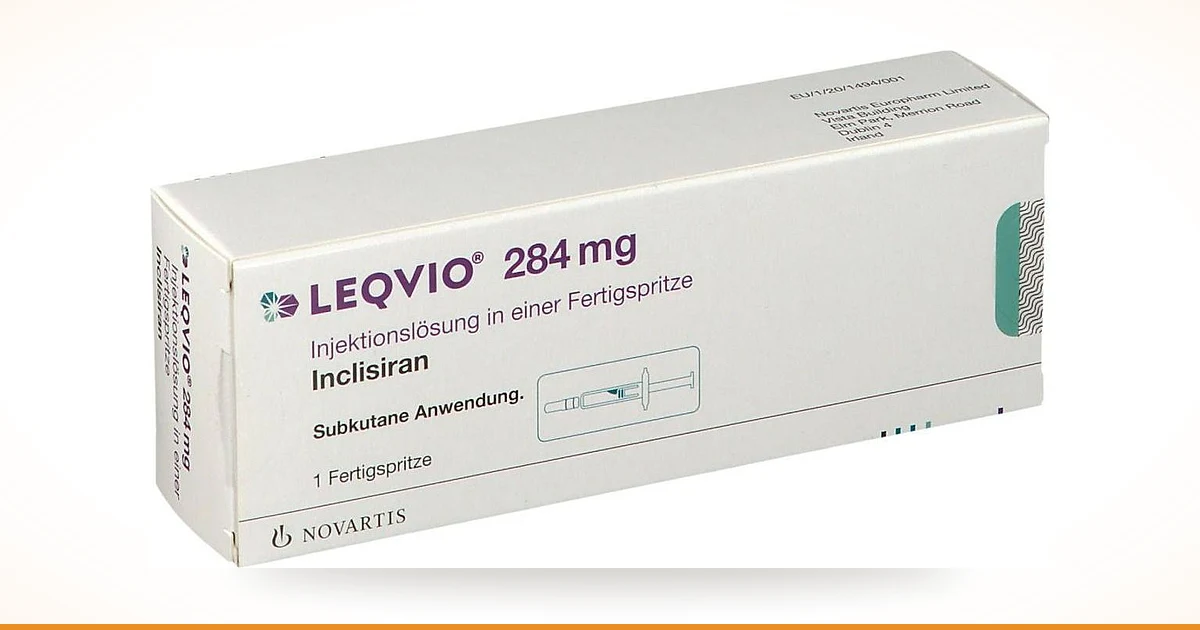
Inclisiran (brand name Leqvio, Novartis) is an injection that lowers "bad" LDL cholesterol by roughly half and is given twice a year: it switches off production of the PCSK9 protein in the liver cell, so the liver clears more LDL from the blood.
| Condition | How it helps | What human studies showed |
|---|---|---|
| Atherosclerotic cardiovascular disease or a risk equivalent, with LDL still high on maximally tolerated statins | added to statins: they reduce cholesterol production, while inclisiran increases its clearance by the liver | ORION-10 and ORION-11, two phase 3 trials: LDL fell by about 50% versus placebo on top of statins [1] |
| Heterozygous familial hypercholesterolaemia — cholesterol high from birth | lowers LDL in a group that responds poorly to standard treatment | ORION-9: LDL fell by about 40% [2] |
| Long-term treatment | two injections a year after the loading doses | ORION-8, extended follow-up: LDL reduction was maintained for years with no sign of waning [3] |
| High LDL and increased risk without a prior vascular event | the FDA allowed use in primary prevention | — |
| Statin intolerance | since 2025 permitted without a background statin, as monotherapy | — |
How it helps
How the liver clears cholesterol from the blood
The liver removes LDL particles — what people call "bad cholesterol" — from the blood. It does so with LDL receptors on its surface: a receptor grabs a particle, pulls it inside, releases the contents and returns to the surface for the next one. The more working receptors, the lower the blood cholesterol.
This system has a regulator: a protein called PCSK9, also made by the liver. It binds the receptor and sends it for destruction rather than recycling. The receptor dies along with the particle it captured, the population of collectors shrinks and blood cholesterol rises.
The therapeutic idea follows directly: remove PCSK9 and receptors live longer. Three generations of agents work on that idea, and they differ in which step they interrupt.
| Approach | Where it acts | Example | How often |
|---|---|---|---|
| Statins | Inhibit cholesterol synthesis in the liver | atorvastatin, rosuvastatin | daily |
| PCSK9 antibodies | Bind the already-made protein in blood | evolocumab, alirocumab | every 2–4 weeks |
| siRNA (inclisiran) | Prevents the protein being made in the liver cell | Leqvio | every 6 months |
How inclisiran works
Inclisiran is a small interfering RNA. This short double-stranded molecule loads into a natural cellular machine called RISC and directs it at one target: the messenger RNA of the PCSK9 gene. Messenger RNA is the working copy of a gene, the instruction from which the ribosome assembles a protein. Destroy the instruction and the protein simply never appears.
The engineering that matters most is delivery. The molecule carries an address: a GalNAc conjugate (N-acetylgalactosamine) recognised by a receptor found almost exclusively on liver cells. The liver is precisely where PCSK9 is synthesised, so the drug works where it is needed rather than across the body.
Why two injections a year suffice. The loaded RISC complex persists inside the cell for a very long time, continuing to destroy newly made copies of the messenger RNA for months. The drug molecule itself has long been cleared while the effect continues — cholesterol lowering depends not on drug concentration in blood but on the production line inside the cell staying switched off.
That is fundamentally different from the familiar logic of "take the tablet, get the effect; skip it, lose the effect".
What the trials showed
ORION-10 and ORION-11 (New England Journal of Medicine, 2020) — two phase 3 trials in patients with atherosclerotic cardiovascular disease or a risk equivalent, already taking maximally tolerated statins [1]. The critical detail: the LDL reduction of about 50% versus placebo was achieved on top of statins, not instead of them — in patients whose cholesterol stays high despite therapy, and there are many of those.
ORION-9 (New England Journal of Medicine, 2020) — patients with heterozygous familial hypercholesterolaemia, a genetic condition with lifelong high cholesterol [2]. A reduction of about 40% is less than in the general group, which is expected: in the familial form the receptors themselves are impaired, so the ceiling is lower. For a population that responds poorly to standard treatment, it is nonetheless substantial.
ORION-8 (Cardiovascular Research, 2024) — extended follow-up of programme participants [3]. It answers a reasonable suspicion: might the liver adapt and route around the block? On the available data, no: LDL reduction was maintained across years of treatment.
Who it is for
The label has widened twice, which changes the picture:
▸ initially — adults with atherosclerotic cardiovascular disease and with familial hypercholesterolaemia, as an addition to statins;
▸ then the FDA allowed use in people with high LDL and increased risk who have not yet had a vascular event — primary prevention;
▸ in 2025 the label widened again: the drug may be used without a background statin, as monotherapy.
That last point matters particularly for patients intolerant of statins, a group whose options have always been narrow.
The general rule still holds: the higher the total risk and the further cholesterol sits from target, the stronger the case for adding the drug. The decision belongs to the clinician, based on LDL, comorbidity and what has already been tried.
How it is administered
| Item | Detail |
|---|---|
| Dose | 284 mg in a prefilled syringe |
| Route | Subcutaneous, usually the abdomen |
| Schedule | Day 0 → 3 months → every 6 months thereafter |
| Who administers | Usually a healthcare professional rather than the patient |
| Monitoring | Lipid profile before starting, then per the clinician's plan |
Two appointments a year address a problem that weighs more heavily in cardiology than it appears: adherence. A substantial share of patients abandon daily tablets within the first year, and a drug you cannot forget to take carries value of its own — provided the appointment happens.
▸ It is not a "cholesterol vaccine". The effect lasts while injections continue; a missed six-month appointment means cholesterol returns, just slowly.
▸ It does not replace lifestyle. Diet, weight, physical activity and smoking influence risk through a dozen mechanisms, not only through LDL.
Who should see a doctor first
▸ It is a prescription medicine, given under medical supervision with lipid monitoring — not a preventive "course".
▸ It is not an automatic reason to stop statins. Monotherapy is permitted but chosen deliberately, most often for intolerance. Abandoning therapy with a proven effect on outcomes in favour of a new drug without discussing it with your clinician is a poor trade.
Side effects. The commonest adverse event is a local reaction at the injection site: redness, tenderness, a firm lump. Usually mild, self-resolving, rarely a reason to stop. Pooled safety analyses have not identified systemic problems specific to the drug [4].
Muscles deserve separate mention. Muscle pain is a common complaint on statins and a common reason for stopping them. Inclisiran's mechanism does not touch muscle tissue, and no such effect is expected.
Bottom line
Inclisiran switches off PCSK9 production in the liver cell, and GalNAc-targeted delivery takes it almost exclusively to where that protein is made. Two injections a year after the loading doses lower LDL by about 50% on top of statins (ORION-10 and ORION-11) and by about 40% in familial hypercholesterolaemia (ORION-9), and the reduction is sustained for years (ORION-8). The label now covers primary prevention and use without a statin; tolerability is good, the main complaint being a local injection-site reaction.
It is worth discussing this drug with your clinician if LDL cholesterol will not reach target on maximally tolerated therapy, if statins are not tolerated, or in familial hypercholesterolaemia. The product can be ordered here — it is prescription-only, administered by a healthcare professional, and a prescription is required.
References
1. Ray KK, et al. Two phase 3 trials of inclisiran in patients with elevated LDL cholesterol (ORION-10 and ORION-11). N Engl J Med. 2020;382(16):1507–1519. PMID 32187462
2. Raal FJ, et al. Inclisiran for the treatment of heterozygous familial hypercholesterolemia (ORION-9). N Engl J Med. 2020;382(16):1520–1530. PMID 32197277
3. Wright RS, et al. Inclisiran administration potently and durably lowers LDL-C over an extended-term follow-up: the ORION-8 trial. Cardiovasc Res. 2024;120(12):1400–1410. PMID 38753448
4. Cicero AFG, et al. Efficacy and safety of inclisiran, a newly approved FDA drug: a systematic review and pooled analysis of available clinical studies. Am Heart J Plus. 2022. PMID 38560059
5. Luo M, et al. Efficacy and safety of inclisiran in stroke or cerebrovascular disease prevention: a systematic review and meta-analysis. Front Pharmacol. 2023. PMID 37383716
Source: Inclisiran (Leqvio): The Twice-a-Year Cholesterol Injection — What Is Proven and What Is Not — universum.earth. Dr. Pereligyn.


