

Key points
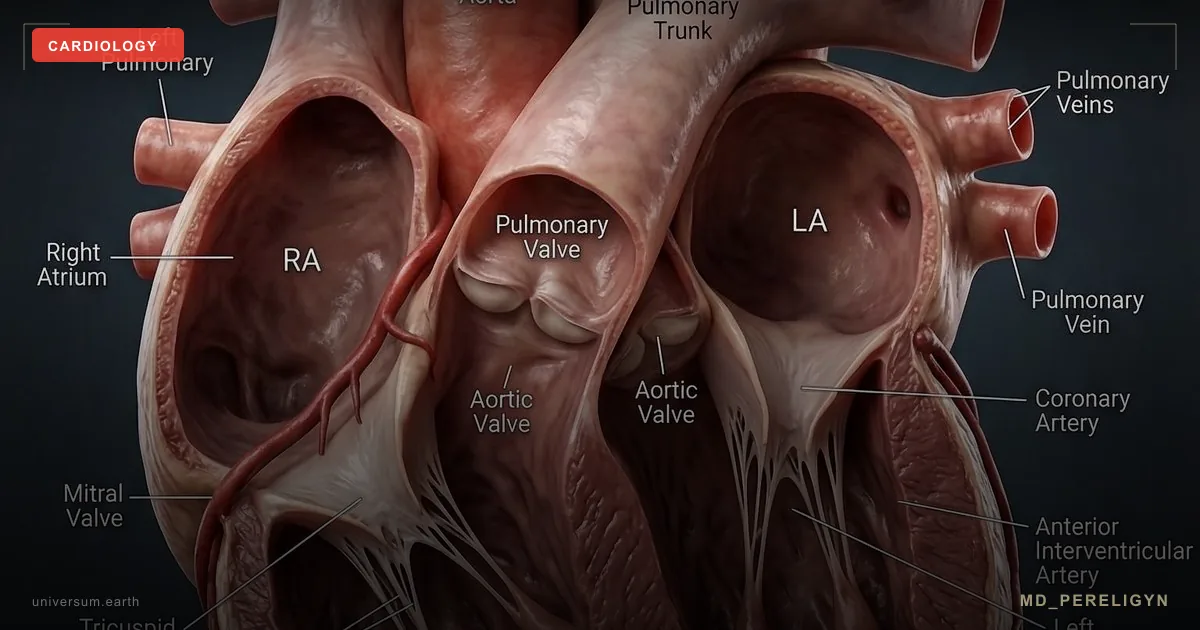
The heart is not only a pump but an endocrine organ: its cells release natriuretic peptides, the body’s own diuretic and vasodilator and a counterweight to the renin–angiotensin–aldosterone system (RAAS). Here is where this system works for people.
| Situation | How it helps | What human studies showed |
|---|---|---|
| NT-proBNP test in dyspnea, edema, fatigue | the most sensitive laboratory marker of heart failure (HF), available in any laboratory | <125 pg/mL (125 ng/L) below age 75 — HF unlikely, negative predictive value above 94%; in acute dyspnea <300 pg/mL (300 ng/L) — 98–99% |
| ARNI (sacubitril/valsartan) in chronic HF | extends the life of the body’s own peptides by blocking the enzyme neprilysin | PARADIGM-HF: cardiovascular death 20% lower than with enalapril |
| SGLT2 inhibitors in HF | unload the heart; NT-proBNP falls | EMPA-REG, DAPA-HF, EMPEROR-Reduced: cardiovascular death and HF hospitalizations 25–35% lower; with ejection fraction ≥50% (EMPEROR-Preserved) — 21% |
| Coenzyme Q10 in chronic HF, alongside standard treatment | a cofactor of heart-muscle energy metabolism | Q-SYMBIO: CoQ10 300 mg/day alongside standard treatment — lower mortality and fewer major cardiovascular events |
| Aerobic training in HF with reduced ejection fraction | trains the heart, improves exercise tolerance | HF-ACTION: death or hospitalization 11% less frequent (after adjustment for prognostic factors), with no increase in adverse events |
| Acute HF in hospital | NT-proBNP dynamics show the response to treatment | a fall of ≥30% by 48–72 hours on loop diuretics is associated with lower 30-day mortality and fewer readmissions |
How it helps
Three peptides, three tasks
- ANP (atrial natriuretic peptide) — produced by atrial cells in response to wall stretch. It acts fast, within minutes: it increases urine output and sodium excretion and dilates vessels.
- BNP (brain natriuretic peptide) — despite its name (it was first isolated from porcine brain), its main source is the cardiac ventricles. Synthesis rises with ventricular overload; its action is longer-lasting.
- CNP (C-type natriuretic peptide) — produced by the endothelium and chondrocytes. A local regulator of vascular tone and bone growth.
All three act through NPR-A and NPR-B receptors, activating guanylate cyclase and increasing intracellular cGMP. The result is vasodilation and sodium excretion. The peptides are degraded by neutral endopeptidase (neprilysin) and through the NPR-C clearance receptor.
What the peptides do in the body
Natriuretic peptides are natural RAAS antagonists: they work in the opposite direction to angiotensin II and aldosterone.
- Natriuresis — more sodium is excreted in urine: the peptides inhibit its reabsorption in the distal tubules.
- Diuresis — urine volume rises through suppression of antidiuretic hormone (ADH) and direct tubular effects.
- Vasodilation — arteriolar smooth muscle relaxes via cGMP.
- RAAS and sympathetic suppression — renin and aldosterone secretion and central sympathetic activity decrease.
- Antifibrotic effect — myocardial myofibroblast proliferation is suppressed.
- Lipolysis — visceral fat breakdown is stimulated through the NPR-A receptor on fat cells. In lean people, BNP is higher than in people with obesity under comparable cardiac load.
When the heart increases synthesis
The main stimulus is wall stretch: volume overload (hypervolemia, valvular regurgitation) or pressure overload (hypertension, aortic stenosis). Levels also rise in heart failure (sustained NT-proBNP elevation is a diagnostic marker), acute myocardial infarction (BNP rises within 24–48 hours), arrhythmias (atrial fibrillation and tachycardia increase ANP), hypoxia (sleep apnea, COPD, pulmonary hypertension), briefly with acute physical exercise, and physiologically in the third trimester of pregnancy.
Synthesis or availability of the peptides is reduced by obesity (increased clearance via NPR-C on fat cells), young age and male sex (lower basal levels), and high-dose glucocorticoids.
NT-proBNP: a window into the system
NT-proBNP is the N-terminal fragment of proBNP: half-life 60–120 minutes, stable during collection and storage. BNP is the active peptide itself: half-life 20 minutes, less stable; target <100 pg/mL (100 ng/L), >400 pg/mL (400 ng/L) — high probability of HF. For NT-proBNP and BNP, pg/mL and ng/L are the same number.
| NT-proBNP, pg/mL (= ng/L) | What it means |
|---|---|
| <125 (age <75 years) | chronic HF unlikely |
| 125–450 | gray zone, requires clinical interpretation |
| <300 in acute dyspnea, any age | acute decompensation ruled out |
| >450 (<50 years), >900 (50–75 years), >1800 (>75 years) | high probability of HF (age-specific thresholds of the ICON study: Januzzi JL, Eur Heart J 2006, PMID 16293638) |
Thresholds are refined by adjusting for age, sex, body mass index (BMI), kidney function, and rhythm:
- Age. Every 10 years, median NT-proBNP rises by 50–100 pg/mL (50–100 ng/L) even without heart disease; a single 125 pg/mL (125 ng/L) threshold in older people gives false-positive results in 40–60% of those tested.
- Sex. Peptide levels are higher in women than in men of the same age (Redfield MM, JACC 2002, PMID 12225726). In women of reproductive age, median NT-proBNP is 40–50% higher; after menopause the gap narrows but does not disappear.
- Weight. In people with acute HF, the higher the BMI, the lower the peptide levels (Krauser DG, Am Heart J 2005, PMID 15990762). With BMI >30 kg/m², NT-proBNP and BNP are 30–50% lower than the true myocardial load. Therefore, with BMI >35 kg/m², NT-proBNP >300 pg/mL (300 ng/L) warrants cardiac imaging at any age.
- Kidneys. NT-proBNP is cleared mainly by the kidneys: at eGFR 30–60 mL/min/1.73 m² the median is 2–3 times higher, at eGFR <30 it is 4–6 times higher. In the van Kimmenade study, at eGFR <60 mL/min/1.73 m² the acute HF thresholds rose from 450 to 1200 pg/mL (ng/L) below age 50 and from 1800 to 4502 pg/mL (ng/L) above age 75. In CKD stage 3b–4, NT-proBNP of 1500–2500 pg/mL (ng/L) does not necessarily mean decompensation; on dialysis, levels without decompensation can exceed 1000 pg/mL (1000 ng/L), and the baseline can even be above 5000 pg/mL (5000 ng/L) without active HF. Comparison with the person’s own baseline matters more here: a rise from 1800 to 4000 pg/mL (from 1800 to 4000 ng/L) is clinically significant. The combination of NT-proBNP >125 pg/mL (125 ng/L) and a urine albumin/creatinine ratio >30 mg/g (3 mg/mmol) increased 5-year HF risk 3.4-fold (PREVEND), so with elevated NT-proBNP this ratio is measured annually.
- Atrial fibrillation itself raises NT-proBNP 2–5-fold even with preserved cardiac function; working thresholds are >900 pg/mL (900 ng/L) below age 75 and >1800 pg/mL (1800 ng/L) above 75. After successful cardioversion, the level falls by 30–60% within 1–2 weeks.
- Other causes without HF: sepsis (3–10-fold, often >1000 pg/mL (1000 ng/L), normalizing with recovery), pulmonary embolism (PE), pulmonary hypertension, severe pneumonia, anemia (hemoglobin <100 g/L (10 g/dL)), hyperthyroidism, Cushing’s syndrome, burns and major surgery, anthracycline chemotherapy, trastuzumab, immune checkpoint and tyrosine kinase inhibitors, and intense exercise the day before (the rise lasts 24–72 hours).
Before referral to a cardiologist or escalation of treatment, the minimum is creatinine and eGFR, complete blood count, TSH, liver function tests, and a history of recent illness, exercise, and medications.
Other markers
- MR-proANP — a stable proANP fragment (≥48 hours in plasma). It depends less on fat tissue and does not change with ARNI treatment, so it helps in obesity and on ARNI. In healthy people it is <86 pmol/L; in acute dyspnea in the emergency department, a threshold of ≥120 pmol/L detected acute HF with 97% sensitivity and 60% specificity (BACH study).
- High-sensitivity troponin (hsTnT/hsTnI) — a marker of myocardial microinjury; together with NT-proBNP it gives the full picture. Outside acute coronary syndrome, hsTnT >14 ng/L (14 pg/mL) in women and >22 ng/L (22 pg/mL) in men indicates occult injury; in the ARIC cohort, hsTnT >14 ng/L (14 pg/mL) combined with NT-proBNP >125 pg/mL (125 ng/L) increased 10-year HF risk 8.2-fold. On hemodialysis, hsTnT is chronically elevated in 80% of patients.
- ST2 and galectin-3 — markers of fibrosis and remodeling, prognostically independent of NT-proBNP. sST2 does not depend on BMI, age, or kidney function, which makes it useful in obesity and kidney disease; its prognostic threshold is 35 ng/mL, and in the PRIDE study each 1 ng/mL increase in sST2 raised annual mortality by 1.4%. Galectin-3 is especially informative in HF with preserved ejection fraction: a level >17.8 ng/mL is associated with a 4-fold risk of HF hospitalization over 4 years.
Together, the markers distinguish a hemodynamic (NT-proBNP), ischemic (troponin), and fibrotic (sST2, galectin-3) pathway, and treatment depends on which one leads.
Drugs that amplify the body’s own system
ARNI (sacubitril/valsartan) block neprilysin and extend the life of the patient’s own peptides; the valsartan component blocks angiotensin II receptors. In PARADIGM-HF, cardiovascular death was 20% lower than with enalapril (McMurray JJV, NEJM 2014, PMID 25176015). On ARNI, NT-proBNP falls by 25–40% over 4–12 weeks, while BNP may rise — it is itself degraded by neprilysin — so treatment is monitored by NT-proBNP or MR-proANP. In the PIONEER-HF analysis, an NT-proBNP fall of >30% from baseline was associated with a 59% reduction in mortality.
SGLT2 inhibitors (empagliflozin, dapagliflozin, canagliflozin) were developed as glucose-lowering drugs, but in EMPA-REG, DAPA-HF, and EMPEROR-Reduced (PMID 32865377) they reduced cardiovascular death and HF hospitalizations by 25–35% — an effect not explained by glucose control. One of the mechanisms is modulation of the natriuretic peptide axis.
They cause osmotic diuresis, reduce plasma volume by 7–10%, and unload the left ventricle, so NT-proBNP synthesis falls; water is lost mainly from the interstitial space (~25% versus ~5% from plasma), which is why symptomatic hypotension is rare. In DAPA-HF, dapagliflozin 10 mg/day with ejection fraction ≤40% lowered median NT-proBNP by 303 pg/mL (303 ng/L) over 8 months; the effect did not depend on glucose level — it was seen in people without diabetes too (PMID 31535829). EMPEROR-Reduced showed the same for empagliflozin 10 mg/day: the fall in NT-proBNP went together with improvement in NYHA functional class and a lower risk of hospitalization.
When treatment of compensated HF begins, NT-proBNP falls by 15–30% over 2–3 months — a sign of cardiac unloading, not a reason to stop the drug. Retest after 3 months, then every 6 months. If NT-proBNP does not fall or rises, the diagnosis is reviewed, adherence is checked, and another cause is sought: anemia, atrial fibrillation, progression of valve disease. Per the 2023 ESC guidelines, SGLT2 inhibitors are indicated at any ejection fraction: ≤40% (HFrEF), 41–49% (HFmrEF), and ≥50% (HFpEF). With preserved ejection fraction, empagliflozin 10 mg/day in EMPEROR-Preserved reduced cardiovascular death or HF hospitalization by 21% regardless of diabetes, and DELIVER confirmed this for dapagliflozin 10 mg/day.
The full regimen in reduced ejection fraction is ARNI + SGLT2 inhibitor + mineralocorticoid receptor antagonist (MRA) + beta-blocker. According to meta-analyses, this quadruple therapy reduces mortality by 73% versus no treatment and by 47% versus a triple regimen without an SGLT2 inhibitor. In HFmrEF (ejection fraction 41–49%), treatment is close to that for HFrEF: ARNI, beta-blockers, MRA, and SGLT2 inhibitors.
Acute dyspnea: a step-by-step assessment
- Step 1 — rule out. NT-proBNP <300 pg/mL (300 ng/L) at any age rules out acute decompensation with a negative predictive value of 98% (ICON, PMID 16293638); BNP <100 pg/mL (100 ng/L) is comparable. The search then turns to the lungs, infection, or metabolism.
- Step 2 — rule in. Above the age-specific thresholds of 450/900/1800 pg/mL (ng/L), adjusted for BMI and eGFR, the positive predictive value is 76–88%: urgent echocardiography, volume assessment, and a loop diuretic are needed.
- Step 3 — gray zone (NT-proBNP 300–450, 450–900, or 900–1800 pg/mL (ng/L), depending on age). Lung ultrasound (B-lines — a sign of interstitial edema), echocardiography with E/e′, jugular venous pressure assessment, chest X-ray, and always troponin are needed: a joint rise of NT-proBNP and troponin points to acute coronary syndrome or myocarditis, while an isolated troponin rise without NT-proBNP is the typical picture of a small, non-Q-wave infarction without decompensation.
- Step 4 — PE. Pulmonary embolism raises both markers through right ventricular overload; when suspected, D-dimer, CT pulmonary angiography, and right ventricular echocardiography are mandatory. In PE, NT-proBNP >600 pg/mL (600 ng/L) identifies intermediate-risk patients (Lankeit M, Eur Respir J 2014, PMID 24627529).
In hospital, a fall in NT-proBNP of ≥30% by 48–72 hours on loop diuretics is associated with lower 30-day mortality and fewer readmissions; if there is no fall or the level rises, treatment is reconsidered: ARNI or inotropic support is added, and mechanical circulatory support is considered. The pre-discharge level is the person’s own reference point for follow-up. After discharge, failure of NT-proBNP to fall by 30% within 30 days predicts a 2–3-fold higher risk of readmission within 90 days — such a patient needs closer follow-up and dose optimization.
Gray zone and repeat testing
At 125–450 pg/mL (125–450 ng/L), the test is repeated in 2–4 weeks under stable conditions (no recent illness, no exercise within 24 hours, no IV fluids). If symptoms persist — echocardiography (ejection fraction, diastolic function by E/e′, left atrial volume index, right ventricle) and high-sensitivity troponin. The H2FPEF (Reddy YNV, Circulation 2018, PMID 29792299) and HFA-PEFF (PMID 31504452) scores build NT-proBNP into the probability of HF with preserved ejection fraction and reduce overdiagnosis in people with obesity, hypertension, and older age. HFA-PEFF criteria: E/e′ >9 (septal), tricuspid regurgitation velocity >2.8 m/s, left atrial volume index >34 mL/m². With ejection fraction ≥50%, atrial fibrillation, pulmonary hypertension, hypertrophic cardiomyopathy, and cardiac amyloidosis (serum light chains, immunofixation, 99mTc-PYP scintigraphy) are also checked.
The intrinsic variability of NT-proBNP is about 30%: a change of at least 30% is considered significant, 50% more reliably so. Without symptoms in the gray zone, the test is repeated in 6–12 months: in the morning, fasting, with no exercise within 24 hours and no acute illness within 2 weeks. On HFrEF treatment — at baseline and 3 months after each titration step; if there is no fall of at least 30%, it is a reason to switch to ARNI or refer to a specialist.
How to support the peptide factory
Principle of the md_pereligyn protocol: the natriuretic system is a modifiable resource. Lifestyle and nutraceuticals support peptide synthesis, receptor sensitivity, and clearance.
- Reduce visceral fat. Weight loss of 5–10% increases basal BNP and NPR-A receptor sensitivity. Helpful: a Mediterranean or DASH diet (olive oil, fish, vegetables, legumes), strength training 2–3 times a week, intermittent fasting 14:10 or 16:8 (improves HOMA-IR and reduces fat mass).
- Keep blood pressure <130/80. This reduces chronic myocardial overload and stabilizes BNP within the physiological range; treating sleep apnea removes nocturnal hypoxia and BP surges. The full protocol is in the BP article.
- Move every day. Walking 7–10 thousand steps a day provides sustained stimulation of BNP synthesis and receptor sensitivity; aerobic activity 30+ minutes a day (swimming, cycling); HIIT 1–2 times a week in cardiovascularly stable people improves VO2max and myocardial remodeling.
- Match exercise to ejection fraction. With preserved function and risk factors — 150 minutes a week of moderate exercise at 60–70% of heart rate reserve plus two strength sessions; intervals of 4 × 4 minutes at 85–95% of peak heart rate with 3 minutes of recovery give about 15% greater gain in peak VO₂ than moderate continuous training. In HFrEF — following HF-ACTION: 36 supervised sessions (60–70% of heart rate reserve), then 5 home sessions a week of 40 minutes; strength work at 50–60% of one-repetition maximum without straining. In HFpEF, 12 weeks of interval or moderate continuous training increased peak VO₂ by about 1.5 mL/kg/min (OptimEx-Clin, Ex-DHF); moderate training is easier to keep up.
- Omega-3 EPA+DHA 2 g/day — reduction of pressure overload, antifibrotic effect, support of cardiomyocyte membranes. The omega-3 index is checked every 4–6 months, target >8%; an index <4% is associated with a 10-fold higher risk of sudden cardiac death. Choose fish oil tested for oxidation (TOTOX <26).
- Magnesium, taurine, potassium. Magnesium (glycinate or taurate) 400 mg/day — a cofactor for cGMP synthesis that relaxes vessels; taurine 1–3 g/day — modulates cardiomyocyte calcium handling, cardioprotection in chronic HF; potassium 4–5 g/day from food — leafy greens, avocado, legumes.
- CoQ10 and mitochondria. Ubiquinol (CoQ10) 100–200 mg/day — a cofactor of myocardial oxidative phosphorylation; in the Q-SYMBIO trial in chronic HF, CoQ10 300 mg/day added to standard treatment reduced mortality (Mortensen SA, JACC Heart Fail 2014, PMID 25282031). L-carnitine 1–2 g/day transports fatty acids into mitochondria; D-ribose 5–10 g/day is a substrate for ATP synthesis when ejection fraction is reduced.
- Vitamins D and K2. Vitamin D3 — to a level of 50–80 ng/mL (125–200 nmol/L), doses of 2,000–5,000 IU/day individualized; vitamin K2 (MK-7) 100–200 mcg directs calcium into bone and protects against valve and vascular calcification.
- Sleep and parasympathetic tone. Sleep of 7–9 hours is a window for hormonal recovery and restoration of receptor sensitivity: chronic sleep deprivation and stress raise sympathetic tone and RAAS activity. Slow diaphragmatic breathing (6 cycles a minute) for 10–20 minutes a day reduces preload; heart rate variability (HRV) biofeedback increases parasympathetic tone.
Who should see a doctor first
See a doctor if you have any of these:
- dyspnea with minimal exertion or at rest;
- leg swelling, especially in the evening;
- nocturnal cough, orthopnea (needing to sit upright to breathe);
- fatigue and an abrupt reduction in exercise tolerance;
- NT-proBNP >125 pg/mL (125 ng/L) or above age-adjusted thresholds;
- previous myocardial infarction or atrial fibrillation;
- family history of chronic HF or sudden cardiac death;
- type 2 diabetes for >10 years — screening for occult HF.
Medications
- Do not stop ARNI or ACE inhibitors on your own in chronic HF — abrupt withdrawal can cause decompensation.
- ARNI require monitoring of eGFR, potassium, and blood pressure every 2 weeks during the first 3 months; they are contraindicated at eGFR <30 mL/min/1.73 m²: such patients were not enrolled in PARADIGM-HF (PMID 25176015). When switching from an ACE inhibitor to ARNI, a 36-hour washout is mandatory because of the risk of angioedema.
- Chronic high-dose NSAIDs inhibit prostaglandins, increase sodium retention, and work against the peptides.
Nutraceuticals: interactions and monitoring
- Omega-3 at 2 g/day modestly prolongs bleeding time and may interact with anticoagulants (warfarin, direct oral anticoagulants) and antiplatelets; at doses >3 g/day on warfarin, INR is monitored, and in people on anticoagulants bleeding events increase slightly. High doses are not prescribed with active bleeding, surgery within 2 weeks, or fish allergy. Atrial fibrillation incidence increased with icosapent ethyl 4 g/day (REDUCE-IT, STRENGTH); this was not consistently seen with 2 g/day of mixed EPA+DHA.
- CoQ10 reduces the effect of warfarin (INR may fall by 10–25%) — recheck INR 1–2 weeks after starting. CoQ10 modestly lowers systolic blood pressure (by 3–5 mmHg) and may potentiate antihypertensive drugs.
- Magnesium at 400 mg/day is well tolerated with normal kidney function but accumulates in CKD stage 3b or worse (eGFR <45 mL/min/1.73 m²): excess causes bradycardia, hypotension, and, at blood levels >2.5 mmol/L (>6.1 mg/dL), neuromuscular paralysis. Separate magnesium from bisphosphonates, tetracyclines, and levothyroxine by 4 hours.
- Vitamin K2 directly antagonizes warfarin and is contraindicated with vitamin K antagonists; it does not interact with direct oral anticoagulants. Vitamin D3 at 25(OH)D levels >80 ng/mL (200 nmol/L) carries a small risk of hypercalcemia, especially with calcium supplements or thiazide diuretics: check calcium and 25(OH)D 3 months after starting, then annually.
- Taurine at 1–3 g/day is the safest on the list, but is best avoided in bipolar disorder and severe hepatic impairment. None of these nutraceuticals is started within 48 hours of cardiac surgery without the surgical team’s approval.
Exercise
- It is reasonable to start if, at rest, systolic blood pressure is below 180 and above 90 mmHg, heart rate is below 100 bpm, NT-proBNP is stable on repeat measurements, and there has been no exertional syncope, ventricular arrhythmia, or unstable angina in the past 6 weeks.
- Stop the session and see a doctor if you have chest pain or pressure not relieved by rest, breathlessness when lying down at night on training days, weight gain of more than 2 kg in 3 days, or a resting heart rate above 100 bpm. With an implanted defibrillator, keep heart rate 10 bpm below its detection zone.
Bottom line
The heart is an endocrine organ. Atrial and ventricular cells produce ANP and BNP, the body’s own diuretic and vasodilator and a counterweight to RAAS, working around the clock. NT-proBNP in a routine laboratory is a window into this system: a level <125 pg/mL (125 ng/L) with age adjustment indicates preserved function, and elevation is an early signal of occult HF long before symptoms.
Reducing visceral fat, blood pressure control, aerobic exercise, omega-3, magnesium, taurine, CoQ10, vitamins D and K2, and sleep support peptide synthesis and receptor sensitivity. ARNI and SGLT2 inhibitors amplify the patient’s own system — this is how modern pharmacology copies the body’s physiology. Treatment should target regulation, not only symptoms.
I perform comprehensive cardiovascular screening (NT-proBNP, hsTnT, echocardiography with functional assessment, extended metabolic profile) and create a personalized protocol to support the natriuretic system.
Sources
▸ de Bold AJ, Borenstein HB, Veress AT, Sonnenberg H. A rapid and potent natriuretic response to intravenous injection of atrial myocardial extract in rats. Life Sci 1981;28:89–94. PMID 7219045
▸ Levin ER, Gardner DG, Samson WK. Natriuretic peptides. NEJM 1998;339:321–328. PMID 9682046
▸ McMurray JJV, Packer M, Desai AS, et al. Angiotensin-neprilysin inhibition versus enalapril in heart failure. NEJM 2014;371:993–1004. PMID 25176015
▸ Mortensen SA, Rosenfeldt F, Kumar A, et al. The effect of coenzyme Q10 on morbidity and mortality in chronic heart failure: results from Q-SYMBIO. JACC Heart Fail 2014;2:641–649. PMID 25282031
▸ Ponikowski P, Voors AA, Anker SD, et al. 2016 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur Heart J 2016;37:2129–2200. PMID 27206819
▸ Heidenreich PA, Bozkurt B, Aguilar D, et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure. J Am Coll Cardiol 2022;79:e263–e421. PMID 35379503
Related articles: Endothelium: foundation of vascular health, Cholesterol without statins.
What does NT-proBNP show?
It is the most sensitive laboratory marker of heart failure (HF). A level <125 pg/mL (125 ng/L) below age 75 makes HF unlikely, with high negative predictive value. Exceeding age-adjusted thresholds calls for echocardiography and assessment of cardiac structure. The marker is also used to monitor treatment: a reduction in NT-proBNP during therapy is associated with a better prognosis.
Why can NT-proBNP be normal in a person with obesity despite obvious HF?
Fat cells carry NPR-C clearance receptors, which accelerate peptide removal from the blood. With BMI >35 kg/m², NT-proBNP is 30–50% lower than the true cardiac load. The result is therefore interpreted with a BMI adjustment or complemented by other methods — MR-proANP and echocardiography.
Can the body’s own natriuretic peptides be supported without drugs?
Yes, partially. Aerobic exercise, reduction of visceral fat, omega-3, magnesium, taurine, and blood pressure control support peptide synthesis and receptor sensitivity. ARNI drugs (sacubitril/valsartan) slow peptide degradation and prolong their life — they work with a molecule the body already makes.
When should NT-proBNP be ordered?
In dyspnea of unclear origin, edema, suspected occult HF in the setting of diabetes or hypertension, before major surgery, or with a family history of chronic HF before age 60. In metabolic syndrome or type 2 diabetes lasting >10 years, the test is justified. Routine screening is not indicated in a young healthy person without symptoms.
How does ARNI differ from a standard ARB?
ARNI (sacubitril/valsartan) combines a neprilysin inhibitor, which increases levels of the body’s own natriuretic peptides, with an ARB, which blocks angiotensin II. In PARADIGM-HF, cardiovascular death was 20% lower than with enalapril (McMurray 2014, PMID 25176015). It is an example of a drug amplifying the body’s own system rather than replacing it.
Why does NT-proBNP fall on SGLT2 inhibitors?
These drugs remove excess fluid and unload the left ventricle, so the heart produces less NT-proBNP. When treatment of compensated HF begins, the level falls by 15–30% over 2–3 months — a sign of unloading, not a reason to stop the drug. Retest after 3 months, then every 6 months.
Source: The heart as a peptide factory: ANP, BNP, CNP, and the endogenous pharmacopoeia — universum.earth. md_pereligyn — Перелыгин Владимир Игоревич.


