

Key points
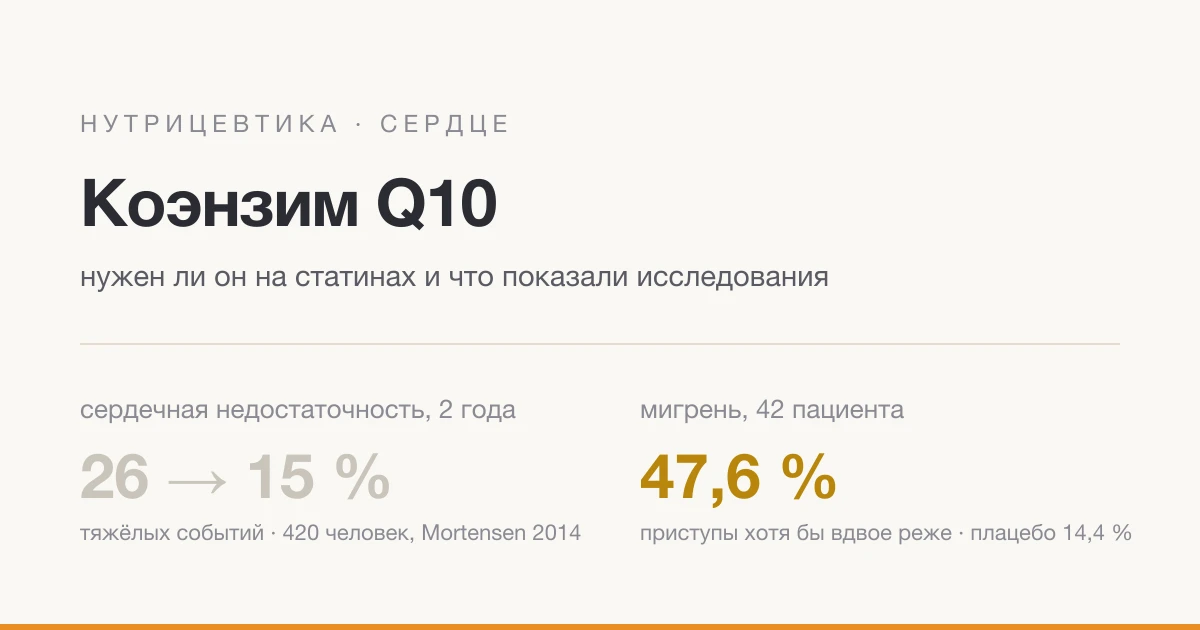
Heart failure: likely benefit. In the Q-SYMBIO study, 420 people with moderate to severe heart failure received Q10 at 100 mg 3 times a day or placebo on top of usual treatment for 2 years. Serious cardiovascular events occurred in 15% versus 26% on placebo (Mortensen SA JACC Heart Fail 2014. PMID 25282031). Cochrane review: probably lower mortality (1 study, 420 people) and fewer hospitalizations for heart failure (2 studies); there is no convincing evidence for or against (Al Saadi T Cochrane Database Syst Rev 2021. PMID 35608922).
Migraine: an encouraging result. In a small study of 42 patients, Q10 at 100 mg 3 times a day worked better than placebo by the third month: attack frequency fell by at least half in 47.6% versus 14.4% (Sándor PS Neurology 2005. PMID 15728298).
Statins lower Q10 levels. Statins slow the formation of mevalonic acid, which is needed to make coenzyme Q10, so its blood level usually falls on statins (Deichmann R Ochsner J 2010. PMID 21603349).
Muscles on statins: the data disagree. A meta-analysis of 12 studies (575 people in total) found less muscle pain, weakness, cramps and fatigue (Qu H J Am Heart Assoc 2018. PMID 30371340), while in a meta-analysis of 7 studies (321 people) no benefit for muscle pain was shown (Kennedy C Atherosclerosis 2020. PMID 32179207).
Blood pressure: no noticeable drop. According to a Cochrane review, there is no clinically significant drop in blood pressure, but the analysis included only 2 studies and 50 people (Ho MJ Cochrane Database Syst Rev 2016. PMID 26935713).
What is coenzyme Q10
Coenzyme Q10 (ubiquinone) is a fat-soluble substance that the body makes itself. It carries electrons in the mitochondria, the cell’s “power plants”, and works as an antioxidant (Al Saadi T Cochrane Database Syst Rev 2021. PMID 35608922).
Burgerstein’s handbook describes its role as cellular energy production and states that the heart, kidneys and liver contain the most Q10 (Burgerstein, Handbuch Nährstoffe 2015, p. 207); the handbook also lists it among antioxidants (Burgerstein, Handbuch Nährstoffe 2015, p. 154). Q10 is made by the body, and there is no intake standard for it.
Why statins lower Q10
Statins lower cholesterol by blocking an enzyme that produces mevalonic acid. But mevalonic acid is also needed to make coenzyme Q10. That is why blood Q10 levels usually fall on statins, and a shortage of Q10 is considered one of the possible mechanisms of muscle pain (Deichmann R Ochsner J 2010. PMID 21603349).
When statins are really needed and when you can do without them is covered in the article Cholesterol: When Statins Are NOT Needed and What Works Instead.
Does Q10 help with muscle pain
Muscle pain on statins is common and makes it harder to continue treatment (Kennedy C Atherosclerosis 2020. PMID 32179207). Meta-analyses answer the Q10 question differently.
There is a benefit. In a meta-analysis of 12 randomized studies (575 people in total), Q10 compared with placebo reduced muscle pain, weakness, cramps and muscle fatigue. The level of creatine kinase (CK), an enzyme that leaks into the blood when muscles are damaged, did not fall (Qu H J Am Heart Assoc 2018. PMID 30371340).
No benefit was shown. In a meta-analysis of 7 studies (321 people), no benefit of Q10 for pain compared with placebo was shown; no difference in the proportion of people who stayed on their statin was shown either (Kennedy C Atherosclerosis 2020. PMID 32179207).
Both meta-analyses largely pooled the same small studies (37–76 participants); the results for pain varied widely between studies (Qu H J Am Heart Assoc 2018. PMID 30371340; Kennedy C Atherosclerosis 2020. PMID 32179207), so a benefit of Q10 for muscle pain on statins has not yet been established.
Heart failure
In Q-SYMBIO, 420 patients with moderate to severe heart failure had Q10 at 100 mg 3 times a day or placebo added to usual treatment for 2 years. The short-term primary endpoints, NYHA severity class (New York Heart Association classification), the 6-minute walk test and NT-proBNP (N-terminal pro-brain natriuretic peptide), did not change significantly at 16 weeks. Serious cardiovascular events over 2 years (the long-term primary endpoint) occurred in 15% versus 26%; among the secondary endpoints, mortality was 10% versus 18%, with fewer hospitalizations for heart failure (Mortensen SA JACC Heart Fail 2014. PMID 25282031).
The 2021 Cochrane review (11 studies, 1573 people) is more cautious: probably lower mortality (1 study, 420 people) and fewer hospitalizations for heart failure (2 studies), moderate-quality evidence. Most studies are small, and there is no convincing evidence for or against Q10 in heart failure (Al Saadi T Cochrane Database Syst Rev 2021. PMID 35608922).
Blood pressure and migraine
Blood pressure. The Cochrane review could pool only 2 studies with 50 participants with primary hypertension. The difference from placebo, systolic −3.68 mm Hg and diastolic −2.03 mm Hg, is not statistically significant. The authors’ conclusion (moderate-quality evidence): no clinically significant effect on blood pressure (Ho MJ Cochrane Database Syst Rev 2016. PMID 26935713).
Migraine. In the study of 42 patients, by the third month on Q10 there were fewer attacks, fewer days with headache and fewer days with nausea, and it was well tolerated (Sándor PS Neurology 2005. PMID 15728298). This is one small study, not a replacement for proven prevention; read about that in the article Migraine: Accurate Diagnosis and Treatment Beyond Painkillers.
Doses and forms
The authors’ range in Burgerstein’s handbook is 30–120 mg a day (Burgerstein, Handbuch Nährstoffe 2015, p. 208); it also states that 60–100 mg a day roughly doubles the blood level of Q10 and that supplements do not suppress the body’s own synthesis (Burgerstein, Handbuch Nährstoffe 2015, p. 208). These are the authors’ regimens, not a recommendation, and current guidelines are more cautious; in Q-SYMBIO and in the migraine study, participants received 300 mg a day (Mortensen SA JACC Heart Fail 2014. PMID 25282031; Sándor PS Neurology 2005. PMID 15728298).
Ubiquinol or ubiquinone. Ubiquinol is the reduced form of Q10. In 12 healthy volunteers, 200 mg of ubiquinol a day raised blood Q10 levels more than the same dose of ubiquinone (Langsjoen PH Clin Pharmacol Drug Dev 2014. PMID 27128225); in 21 people aged 65–74, after a single 100 mg dose the difference was not statistically significant, and Q10 in the blood was mostly in the ubiquinol form, even after taking ubiquinone (Pravst I Nutrients 2020. PMID 32188111). These studies did not measure health benefits.
Safety and warfarin
The handbook calls Q10 well tolerated “in practically unlimited amounts” and attributes stomach complaints to the excipients in the products (Burgerstein, Handbuch Nährstoffe 2015, p. 211). Current data are more cautious: the Q-SYMBIO authors judged 2 years of use to be safe (Mortensen SA JACC Heart Fail 2014. PMID 25282031), but the Cochrane review reached no clear conclusion on side effects, as the evidence is of low quality (Al Saadi T Cochrane Database Syst Rev 2021. PMID 35608922).
Warfarin. Isolated cases have been described in which warfarin worked less well while taking Q10. In a randomized crossover study (24 people, 3 dropped out), Q10 at 100 mg a day was taken for 4 weeks. The international normalized ratio (INR) was kept within 2.0–4.0 per protocol, and the warfarin dose did not need to be changed to achieve this (Engelsen J Ugeskr Laeger 2003. PMID 12772396). The study was small and tested a single dose.
What the studies showed
| What was studied | Who took part | Result |
|---|---|---|
| Muscle pain on statins, meta-analysis, 2018 | 12 studies, 575 people | Less pain, weakness, cramps and fatigue; CK did not fall |
| Muscle pain on statins, meta-analysis, 2020 | 7 studies, 321 people with pain | No benefit for pain compared with placebo was shown; no difference in the proportion staying on a statin was shown |
| Q-SYMBIO, 300 mg a day for 2 years, 2014 | 420 people with heart failure | Serious events in 15% versus 26%, mortality 10% versus 18% |
| Cochrane review, heart failure, 2021 | 11 studies, 1573 people | Probably lower mortality (1 study, 420 people) and fewer hospitalizations (2 studies); no convincing evidence for or against |
| Cochrane review, blood pressure, 2016 | 2 studies, 50 people | No clinically significant reduction |
| Migraine, 300 mg a day for 3 months, 2005 | 42 people | Attack frequency fell by at least half in 47.6% versus 14.4% |
| Warfarin and Q10 100 mg, 4 weeks, crossover, 2003 | 24 people, 3 dropped out | INR was kept within 2.0–4.0; the warfarin dose did not need to be changed |
Not everything is equally proven: for muscle pain on statins the meta-analyses disagree (Qu H J Am Heart Assoc 2018. PMID 30371340; Kennedy C Atherosclerosis 2020. PMID 32179207), for blood pressure no clinically significant effect was found in 50 participants (Ho MJ Cochrane Database Syst Rev 2016. PMID 26935713), and the migraine result comes from one small study (Sándor PS Neurology 2005. PMID 15728298).
Who should be more careful
- People taking warfarin: start or stop Q10 only with your doctor’s knowledge and with INR monitoring.
- People whose muscles hurt on statins: do not stop your statin on your own and do not replace it with a supplement; first discuss the cause of the pain with your doctor.
- If you have severe muscle pain or weakness on statins, see a doctor without delay.
- People with heart failure: Q10 was studied only as an addition to standard treatment, not instead of it.
Bottom line
Statins lower blood Q10 levels, but that does not mean everyone on statins needs Q10: for muscle pain, a benefit has not been established. The most encouraging data come from heart failure, with Q10 added to treatment, and from a small migraine study. Whether you personally need Q10, and whether it is compatible with your medications, can be worked out at a consultation.
This material is for information only and does not replace a doctor’s consultation. Do not stop your statin or change your warfarin dose without your doctor’s approval.


